Health Information Exchange in India: The Future of HIE
Health Information Exchange in India is advancing through ABDM, digital health standards, and national policy frameworks, with the goal of improving care coordination, reducing costs, and enabling interoperable, patient-controlled health data sharing.
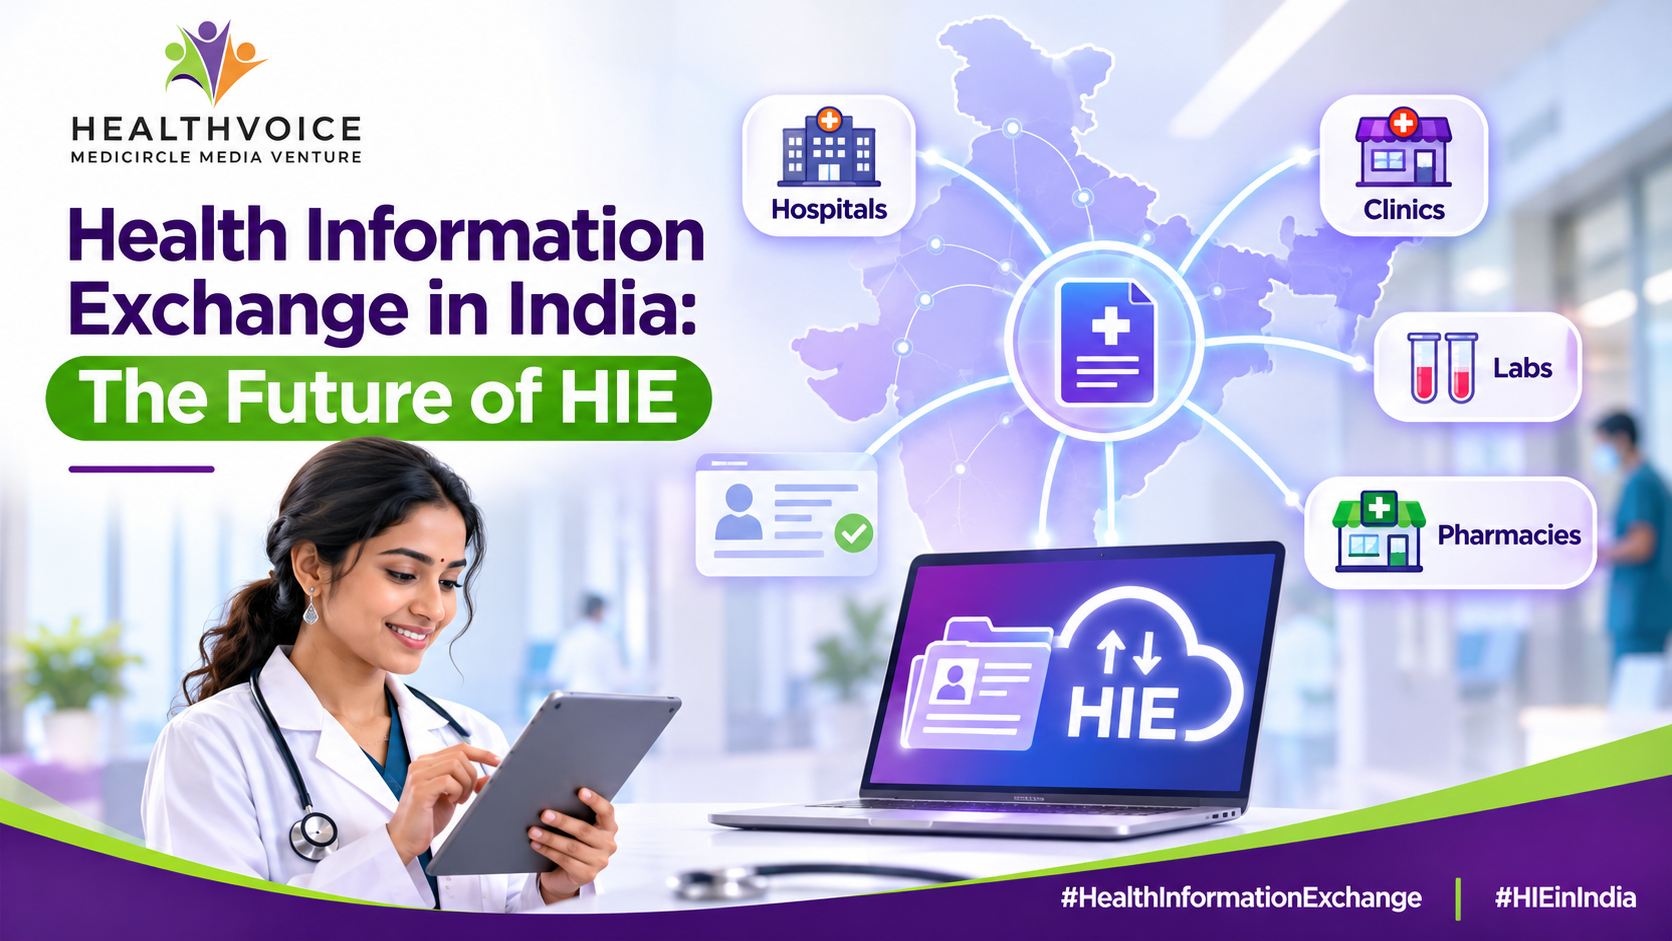
The Future of Health Information Exchange in India
Introduction
India is at a critical turning point in its healthcare journey. With a population of over 1.4 billion people spread across geographically diverse regions, the country has long struggled with fragmented medical records, disconnected care systems, and information gaps that lead to delayed diagnoses, repeated testing, and preventable medical errors. Health Information Exchange, commonly referred to as HIE, is the system-level solution that addresses this core challenge.
Health Information Exchange refers to the electronic movement of health-related information among healthcare organizations, providers, and patients in a secure and standardized manner. It enables doctors, hospitals, diagnostic labs, pharmacies, and insurance providers to access and share patient data seamlessly, reducing duplication of effort and improving the overall quality of care delivered.
India is now building the foundational infrastructure to make this a national reality. The Ayushman Bharat Digital Mission, known as ABDM, launched by the Ministry of Health and Family Welfare, is the primary policy and technology framework driving this transformation. Understanding where India stands today and where it is headed over the next decade is essential for every healthcare professional, policymaker, and healthcare institution in the country.
Understanding Health Information Exchange and Its Core Components
Health Information Exchange is not a single technology but rather a connected ecosystem of standards, platforms, policies, and stakeholders working together to enable the flow of clinical and administrative data. In its most effective form, an HIE system gives an authorized doctor in Bengaluru access to a patient's diagnostic reports from a hospital in Lucknow, without the patient needing to carry physical records or repeat costly investigations.
There are broadly three models through which HIE functions across the world. The first is the directed exchange model, where healthcare providers send and receive patient information securely to and from known parties. The second is the query-based exchange model, where providers actively search for and retrieve patient data from other organizations when needed. The third is the consumer-mediated exchange model, where patients themselves control the flow of their health information among providers.
India's approach under ABDM incorporates elements of all three models, with a strong emphasis on patient consent and data ownership. The Health Data Management Policy under ABDM establishes clear rules about how health data can be accessed, used, and shared, placing significant authority in the hands of the patient through the ABHA, or Ayushman Bharat Health Account, framework.
The Current State of Digital Health Infrastructure in India
India's digital health infrastructure has evolved considerably over the past few years, though significant gaps remain between aspiration and ground-level implementation.
The ABHA number, a unique 14-digit health identifier, now serves as the foundation of India's HIE architecture. As of recent government reports, over 600 million ABHA numbers have been created across the country. Healthcare Professionals Registry and Healthcare Facilities Registry have been established to digitally map doctors and facilities across India. The Unified Health Interface, or UHI, is being developed to allow seamless discovery and booking of health services.
However, challenges persist. A large proportion of healthcare delivery in India still happens through unorganized private clinics, small nursing homes, and rural health sub-centres where digital infrastructure is minimal. Electronic Medical Record adoption among smaller healthcare facilities remains low. Interoperability between different hospital management software systems is limited, and the lack of common data standards has historically made data exchange difficult even among larger institutions.
The government has been working to address these gaps through the HL7 FHIR, or Fast Healthcare Interoperability Resources, standard, which is internationally recognized and now being promoted within ABDM as the technical backbone for data exchange. FHIR-compliant application programming interfaces are being mandated for healthcare software vendors who wish to integrate with the ABDM ecosystem.
Why Health Information Exchange Matters for Indian Patients and Doctors
The case for a robust HIE system in India becomes clearer when one considers the patterns of healthcare utilization across the country. A large number of patients in India consult multiple doctors, often simultaneously, across both public and private healthcare systems. A patient managing diabetes in a government hospital may also visit a private cardiologist and an Ayurvedic practitioner. Without a shared information system, each of these providers makes clinical decisions in isolation, increasing the risk of drug interactions, missed diagnoses, and conflicting treatment approaches.
For doctors, the absence of a reliable HIE system means significant time is spent gathering history and repeat investigations at every consultation. For patients, particularly those from economically vulnerable backgrounds, the cost of repeated diagnostic testing is a significant financial burden. Studies from Indian healthcare settings have consistently shown that duplicate testing and avoidable hospitalisations contribute meaningfully to overall out-of-pocket healthcare expenditure, which remains among the highest in the world relative to income.
A functional HIE system directly addresses these problems. It enables continuity of care, supports better clinical decision-making, reduces unnecessary costs, and helps public health authorities track disease patterns in real time. For doctors engaging with platforms like HealthVoice, which bring together physician voices and healthcare communities, understanding and advocating for HIE is part of a larger professional responsibility to advance the quality and equity of care in India.
Key Policy Frameworks and Government Initiatives Driving HIE in India
India's approach to Health Information Exchange is embedded within a broader national digital health strategy. Several initiatives and frameworks are shaping the direction of this effort.
The Ayushman Bharat Digital Mission, launched in 2021, is the cornerstone of this strategy. It envisions a federated digital health ecosystem where patients own their health data, providers can access it with consent, and public health systems can leverage aggregated, anonymized data for planning and policy.
The National Digital Health Blueprint, developed by the Ministry of Health and Family Welfare in consultation with NITI Aayog and other stakeholders, laid the conceptual groundwork for ABDM by outlining the architecture of a nationwide HIE system built on open standards and federated data models.
The Electronic Health Records Standards for India, originally developed in 2016 and subsequently updated, provide technical guidance to hospitals and software vendors on structuring clinical data in a format that supports exchange and interoperability.
The National Health Policy 2017 also explicitly recognized the need for digital health infrastructure, including electronic health records and health information systems, as integral to achieving universal health coverage.
At the state level, several states, including Andhra Pradesh, Telangana, and Maharashtra, have developed their own health information systems that are now being aligned with ABDM. The Telangana government's T-CHIS and Andhra Pradesh's Dr. YSR Aarogyasri Health Care Trust are examples of state-level systems that have worked toward digitizing health records and improving data access for care coordination.
Challenges Facing Health Information Exchange in India
Despite strong policy intent and early implementation milestones, Health Information Exchange in India faces a set of structural and practical challenges that must be addressed for the system to reach its full potential.
The most significant challenge is the digital divide. While urban India has seen rapid adoption of digital health technologies, rural India and Tier 3 cities face persistent barriers including unreliable internet connectivity, low digital literacy among both patients and small healthcare providers, and lack of affordable devices. Any HIE system that does not account for these realities will remain a tool for the urban privileged rather than a genuinely universal solution.
Data privacy and security concerns represent another major challenge. While the Digital Personal Data Protection Act, 2023 provides a legal framework for data protection in India, its implementation in the healthcare context requires further regulatory clarity. Patients, particularly those with stigmatized conditions such as HIV, mental health disorders, or reproductive health issues, need strong assurance that their health data will be protected and that access will be governed by meaningful consent mechanisms.
Interoperability between legacy hospital information systems remains a technical bottleneck. Many large private hospital chains operate on proprietary software that was not built with open standards in mind. Migrating these systems to FHIR-compliant architectures requires both investment and institutional will.
Provider adoption is also uneven. Many doctors, especially those practicing independently or in small group practices, are unfamiliar with ABDM and do not yet see a direct benefit in their day-to-day practice. Without active outreach, education, and incentives for providers, the ecosystem will remain fragmented regardless of the technological infrastructure in place.
The Road Ahead: Emerging Trends Shaping HIE in India
The future of Health Information Exchange in India is being shaped by several converging trends that have the potential to accelerate progress significantly over the next five to ten years.
Artificial intelligence and machine learning are beginning to play a meaningful role in clinical decision support, population health management, and predictive analytics. When these technologies are connected to a rich, interoperable health data ecosystem, they can identify at-risk populations, flag potential drug interactions, and support diagnosis in resource-limited settings. India's large and diverse patient population represents a unique asset for training AI models that are relevant to South Asian disease patterns.
Telemedicine has expanded dramatically following the COVID-19 pandemic and the introduction of the Telemedicine Practice Guidelines by the Medical Council of India in 2020. Telemedicine works best when doctors can access a patient's digital health history at the point of a virtual consultation. As HIE infrastructure matures, telemedicine platforms will become significantly more clinically effective.
The National Medical Register, being developed under the National Medical Commission, will eventually link physician credentials to the ABDM ecosystem, further strengthening the trust and authentication layer of Health Information Exchange.
Wearable health devices and remote patient monitoring tools are increasingly finding their way into Indian homes, particularly in urban markets. Integrating the data generated by these devices into the national HIE framework will require new data standards, privacy safeguards, and clinical workflows.
Frequently Asked Questions
Q1: What is Health Information Exchange and why is it important for India?
Health Information Exchange is the secure electronic sharing of patient health information among healthcare providers, hospitals, labs, and other stakeholders. For India, it is important because the healthcare system is highly fragmented, with patients consulting multiple providers in both public and private sectors. A functioning HIE system reduces duplicate testing, improves care coordination, lowers costs, and enables better public health surveillance.
Q2: How does ABDM support Health Information Exchange in India?
The Ayushman Bharat Digital Mission provides the policy framework, technical standards, and infrastructure for Health Information Exchange in India. It enables patients to create an ABHA number as a unique health identifier, registers healthcare providers and facilities, and promotes FHIR-based interoperability to allow different health systems to communicate securely with patient consent.
Q3: What are the biggest challenges to implementing HIE in India?
The major challenges include the digital divide between urban and rural areas, low adoption of electronic medical records among smaller healthcare providers, concerns about data privacy and security, lack of interoperability between existing legacy hospital systems, and limited awareness and incentives for physician adoption of digital health tools.
Q4: How does HIE protect patient data and privacy in India?
India's HIE framework under ABDM operates on a consent-based model, meaning health data can only be accessed by providers with explicit patient authorization through Health Locker applications and consent managers. The Digital Personal Data Protection Act, 2023 provides the broader legal framework for personal data protection, including health data.
Q5: What role do doctors and medical associations play in advancing HIE in India?
Doctors and medical associations are essential stakeholders in HIE adoption. They need to actively participate in ABDM by linking their credentials to the Healthcare Professionals Registry, encouraging patients to create ABHA numbers, adopting FHIR-compliant practice management software, and advocating within their communities for the clinical and systemic benefits of Health Information Exchange. Platforms like HealthVoice play a meaningful role in facilitating these professional conversations and enabling collective advocacy.
Resources
- Ayushman Bharat Digital Mission (ABDM): Official government portal for India's national digital health ecosystem, including ABHA, HIE standards, and implementation guidelines.
- Ministry of Health and Family Welfare, Government of India: Central repository for national health policy documents, including the National Health Policy 2017 and EHR Standards for India.
- National Health Authority (NHA): The apex body responsible for implementing ABDM, with resources on FHIR standards, Healthcare Professionals Registry, and Healthcare Facilities Registry.
- World Health Organization, India Country Office: WHO guidance and reports on digital health, health information systems, and health data governance relevant to the Indian context.
- Indian Council of Medical Research (ICMR): Publications on digital health research, health data standards, and evidence-based studies related to healthcare delivery and information systems in India.
Interlinking Keywords
Ayushman Bharat Digital Mission, ABHA health ID, electronic health records India, digital health interoperability, FHIR standards India, national health policy India, telemedicine India, healthcare data privacy India, Healthcare Professionals Registry, public health surveillance India
Last reviewed by:
Dr. Manthan Tripathi, HealthVoice Editorial and Medical Advisory Team, November 11, 2026.
Disclaimer
This article is intended for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional medical consultation. The information presented here reflects publicly available policy documents, government initiatives, and healthcare system-level discussions. Individual clinical decisions should always be made in consultation with qualified healthcare professionals. HealthVoice does not endorse any specific technology vendor, software platform, or healthcare service provider mentioned or implied in this content.
 Dr. Manthan Tripathi
#HealthInformationExchange #HIEinIndia
