Why Doctors Must Lead Health Policy in India
Doctors in India must be recognized as essential contributors to healthcare policy. Strengthening physician participation in governance is fundamental to building a more effective and trustworthy health system.

Why Doctors Need a Stronger Voice in Health Policy
Introduction
India is at a defining moment in its healthcare journey. With a population of over 1.4 billion, a rapidly rising burden of non-communicable diseases, persistent gaps in rural healthcare access, and an increasingly complex health infrastructure, the decisions made in policy corridors today will shape the health of millions for decades to come. Yet those who understand the ground realities most deeply, the doctors and frontline medical professionals, remain largely absent from the rooms where those decisions are made.
This absence is not simply an oversight. It reflects a systemic gap that has long limited the effectiveness of India's public health policies. Policies designed without adequate physician input often fail to address real clinical challenges, underestimate implementation barriers, and fall short of delivering meaningful outcomes. The need for doctors to assume a stronger, more organized, and more credible role in health policy is no longer a matter of professional ambition. It is a matter of public interest.
The Current State of Physician Participation in Indian Health Policy
India has several established bodies that influence healthcare governance. The National Medical Commission, the Indian Council of Medical Research, the Ministry of Health and Family Welfare, and state-level directorates all play significant roles in shaping health policy. However, the meaningful participation of practicing clinicians, particularly those working in district hospitals, rural health centres, and urban secondary care settings, remains limited.
Policy committees tend to be populated by administrators, economists, public health academics, and political representatives. While each of these stakeholders brings valuable perspectives, the clinical voice, rooted in patient interaction, disease management, and healthcare delivery realities, is often underrepresented. The result is a policy environment that frequently prioritizes budgetary and administrative considerations over clinical and patient-centered ones.
According to the National Health Policy 2017, India aims to increase public health expenditure to 2.5 percent of GDP. However, translating this ambition into effective healthcare delivery requires the kind of granular clinical insight that only practicing doctors can provide. The gap between policy intention and healthcare outcomes is, in many ways, the gap between administrative planning and medical reality.
Why Doctor Leadership in Health Policy Matters
Clinical Expertise Bridges the Gap Between Policy and Practice
Doctors spend years, often decades, working directly with patients across diverse socioeconomic backgrounds and geographic regions. This experience generates a form of knowledge that cannot be replicated through data reports or administrative audits alone. When a physician working in a government hospital in Uttar Pradesh or a district clinic in Bihar observes systemic failures in drug supply, diagnostic access, or patient referral pathways, that observation carries the weight of lived clinical reality.
Health policies designed with active physician input are more likely to address these on-ground realities, propose workable solutions, and anticipate implementation challenges before they become crises. A doctor who has treated hundreds of patients with drug-resistant tuberculosis understands the protocol gaps far better than a policy document can capture.
The Public Health Dimension
India carries one of the highest burdens of preventable disease in the world. According to ICMR data, non-communicable diseases now account for over 60 percent of all deaths in India. Conditions such as diabetes, hypertension, cardiovascular disease, and mental health disorders are rising sharply, particularly in urban populations and increasingly in rural areas as well.
Effectively addressing this burden requires healthcare policies that move beyond hospital infrastructure and toward prevention, early detection, and community health engagement. Doctors are ideally positioned to advocate for these dimensions, drawing on their direct experience of how late-stage disease presentation is linked to poor preventive health awareness, inadequate screening programs, and limited access to primary care.
Strengthening Trust Between the Medical Community and the State
One of the most visible consequences of doctors being excluded from policy decisions is the erosion of trust between the medical profession and the government. Policy mandates that doctors perceive as disconnected from clinical realities often face resistance during implementation. When healthcare workers feel that rules are being imposed upon them rather than designed with them, compliance suffers and outcomes deteriorate.
Meaningful doctor participation in policy processes creates a sense of shared ownership. It signals respect for clinical expertise and builds a foundation for collaborative healthcare governance. This, in turn, strengthens the broader public trust in health institutions.
Barriers That Keep Doctors Out of Policy Spaces
Understanding why doctors are underrepresented in health policy requires acknowledging the structural and cultural barriers that exist.
One significant barrier is time. Practicing physicians in India, particularly those in government healthcare settings, carry extraordinarily heavy patient loads. Finding time to engage with policy processes, attend consultative meetings, prepare submissions, or participate in advisory committees can feel impossible within the demands of a busy clinical schedule.
Another barrier is the absence of organized platforms through which the medical community can aggregate its voice. Individual doctors may hold strong and well-informed views on healthcare policy, but without a credible collective channel, those views rarely reach the people who need to hear them. Medical associations exist across India, but their policy advocacy functions are not always consistent, well-coordinated, or widely visible.
There is also a cultural dimension to consider. Medical education in India emphasizes clinical competence and patient care, which is entirely appropriate. However, it rarely cultivates skills related to policy literacy, advocacy, healthcare economics, or governance. As a result, many doctors feel ill-equipped to engage with policy processes even when opportunities arise.
What a Stronger Doctor Voice in Policy Would Look Like
Structured Representation in Policy Bodies
Meaningful change begins with structural inclusion. Healthcare policy committees, advisory bodies, and working groups at both the national and state level should include practicing clinicians as formal, voting members, not merely as consultants invited to validate decisions already made. The National Medical Commission and state medical councils have a role to play in championing this representation.
Policy Literacy as Part of Medical Education
Medical colleges and postgraduate institutions should incorporate modules on health policy, healthcare economics, medical ethics, and advocacy into their curricula. A doctor who understands how health budgets are allocated, how legislation moves through the system, and how evidence informs policy is far better equipped to contribute meaningfully to governance conversations. Some of the most progressive medical institutions globally have recognized this and built health systems science into their training programs.
Platforms for Collective Medical Voice
Doctors need credible, organized, and respected platforms through which they can communicate their collective observations and recommendations to policymakers. This is where organizations like HealthVoice can play a genuinely transformative role. By connecting doctors, medical associations, and healthcare communities through structured communication and professional engagement, platforms like HealthVoice create the infrastructure through which clinical voices can be amplified, organized, and directed toward the people shaping India's health policy landscape.
When doctors can share their on-ground insights, raise concerns about systemic failures, and propose evidence-based solutions through a trusted community platform, those voices have a far greater chance of influencing the decisions that matter.
Collaboration with Public Health Experts and Administrators
A stronger doctor voice in health policy does not mean displacing other stakeholders. India's healthcare challenges are complex and multidimensional. They require economists, public health specialists, community health workers, policymakers, and medical professionals working in genuine collaboration. The goal is not to hand over health policy to doctors alone, but to ensure that clinical expertise is genuinely embedded in the decision-making process, not treated as an afterthought.
Lessons from Global Models of Physician Policy Leadership
Several countries have demonstrated what is possible when doctors are systematically integrated into health policy structures. In the United Kingdom, the National Health Service actively engages clinical leaders through its medical director framework and clinical senates, creating formal pathways for physician input at every level of the health system. In Canada, provincial health authorities work closely with physician associations on policy design, particularly in areas like resource allocation and care delivery models.
In India, there are encouraging precedents as well. The clinical input of infectious disease specialists was invaluable in shaping India's COVID-19 response, particularly in areas of treatment protocols, vaccine rollout strategies, and public communication. The lesson is clear: when doctors are given a meaningful seat at the table, health policy becomes more evidence-based, more practically grounded, and more effective.
The Role of Medical Associations in Policy Advocacy
Medical associations in India, from national bodies to state chapters and specialty societies, are the natural organizational vehicles through which physicians can engage with health policy. Associations carry collective credibility, have established relationships with regulatory bodies and government departments, and can communicate on behalf of a broad community of practitioners.
However, to fulfill this role effectively, medical associations must invest in their policy advocacy capabilities. This means developing dedicated policy research and communication functions, building relationships with legislators and health ministry officials, and creating mechanisms through which their member physicians can submit observations and recommendations systematically.
The connection between strong medical associations and effective health policy is not coincidental. Countries with robust, well-organized professional medical bodies tend to have health systems that are more responsive to clinical realities and more capable of translating evidence into effective practice.
Conclusion
The health challenges facing India are significant, but they are not insurmountable. What they require is a health policy environment that draws on the full depth of expertise available in the medical community. Doctors who serve patients every day, who witness the consequences of policy gaps firsthand, and who understand the clinical dimensions of public health challenges must be recognized as essential contributors to healthcare governance.
Strengthening the doctor's voice in health policy is not about giving physicians more power for its own sake. It is about building a more effective, more responsive, and more trustworthy health system for the 1.4 billion people who depend on it. The platforms, associations, and policy frameworks that enable this participation are not optional features of a well-functioning healthcare ecosystem. They are foundational to it.
As India moves toward achieving universal health coverage and strengthening its public health architecture, the integration of physician leadership into policy design is one of the most impactful steps the country can take. The time for doctors to claim their rightful place in this conversation is now.
Frequently Asked Questions
Q1: Why are doctors not more involved in Indian health policy today?
Doctors in India face significant barriers to policy participation, including heavy patient workloads, limited policy literacy as part of medical training, and the absence of organized platforms through which clinical voices can be collectively directed toward policymakers. Structural exclusion from formal advisory bodies also plays a major role.
Q2: How does doctor participation improve health policy outcomes?
Doctors bring direct clinical experience to policy discussions, helping identify gaps between intended policy goals and actual healthcare delivery realities. Their input makes policies more practical, more evidence-based, and better aligned with the needs of patients and healthcare providers on the ground.
Q3: What role do medical associations play in healthcare policy in India?
Medical associations serve as collective advocacy bodies that can represent the professional views of large communities of doctors. When these associations are well-organized and invest in policy research and communication, they become influential channels through which clinical insights reach government health bodies and legislative decision-makers.
Q4: What changes in medical education could strengthen physician policy engagement?
Introducing modules on health policy, healthcare economics, medical ethics, governance, and advocacy within medical college curricula would help future doctors develop the literacy and confidence needed to engage with policy processes. Understanding how health systems function at the structural level is as important as clinical competence for doctors who wish to contribute to governance.
Q5: How can platforms like HealthVoice support physician policy advocacy in India?
Platforms like HealthVoice create structured, credible digital spaces where doctors, medical associations, and healthcare communities can communicate, share professional insights, and amplify collective voices. By building visibility and enabling organized engagement, such platforms help connect the clinical community with the broader conversations shaping India's health policy direction.
Resources
- Indian Council of Medical Research (ICMR): Guidelines, research publications, and national disease burden data relevant to healthcare policymaking in India.
- World Health Organization (WHO) India Country Office: Reports and frameworks on public health governance, universal health coverage, and physician engagement in policy design.
- Ministry of Health and Family Welfare, Government of India: Official health policy documents, the National Health Policy 2017, and updates on Ayushman Bharat and other flagship programs.
- National Medical Commission (NMC): Regulatory frameworks, medical education guidelines, and professional standards that govern the medical community in India.
- NITI Aayog Health Reports: Strategic analyses and policy recommendations on India's health sector transformation, healthcare financing, and reform priorities.
Interlinking Keywords
doctor voice in health policy, physician leadership India, medical associations India, healthcare governance India, NMC health policy, ICMR public health, health policy reform India, doctor advocacy, clinical leadership, healthcare community platform, medical professional representation, health system India
Last reviewed by:
Dr. Manthan Tripathi, HealthVoice Editorial and Medical Advisory Team, November 5, 2026.
Disclaimer
The content published in this article is intended for informational and educational purposes only. It does not constitute medical advice, clinical guidance, or a substitute for professional medical consultation. The views expressed reflect general perspectives on healthcare policy and physician advocacy and do not represent the official position of any government body, regulatory authority, or medical institution. Readers are encouraged to consult qualified healthcare professionals and official policy sources for specific guidance related to their professional or clinical decisions.
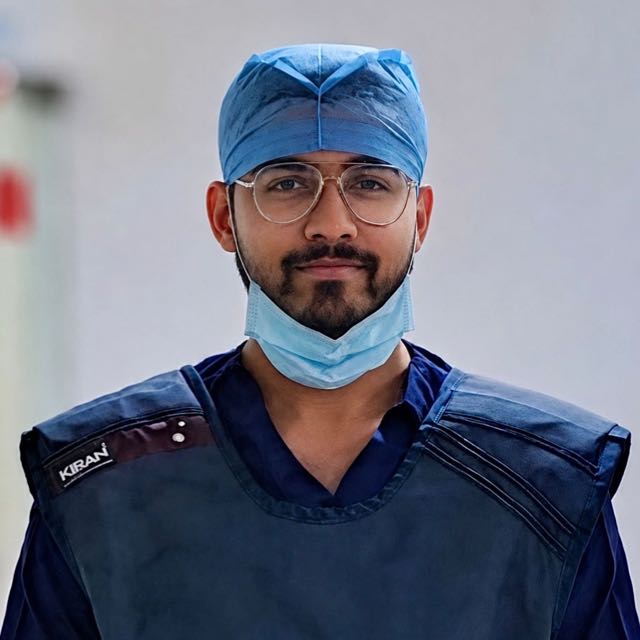 Dr. Manthan Tripathi
#HealthPolicyIndia #DoctorsInPolicy
